
Why hospital wound care and surgical departments are re-evaluating collagen remodeling science — and what it means for procurement decisions in 2026
Introduction
Collagen remodeling is the phase of wound healing that determines whether a wound closes with a functional, low-scar outcome or lingers as a chronic, non-healing ulcer. For corporate hospitals managing high patient volumes across diabetology, vascular surgery, plastic surgery, and wound care units, the quality of this remodeling phase directly affects length of stay, readmission rates, and patient satisfaction scores — all metrics that matter to hospital administrators as much as to clinicians.
At the center of this process sits the extracellular matrix (ECM): the three-dimensional scaffold of proteins, glycoproteins, and growth factors that surrounds every cell in human tissue. Understanding how ECM governs collagen remodeling is no longer a purely academic interest — it is shaping procurement and protocol decisions in advanced wound care departments across India.
What Is the Extracellular Matrix, and Why Does It Matter in Wound Repair?
The ECM is far more than structural packing material. It is a dynamic, biologically active network composed of collagen, elastin, fibronectin, glycosaminoglycans, and a range of growth factors and cytokines. In healthy tissue, the ECM performs several functions simultaneously:
-
Structural scaffolding that gives tissue its mechanical integrity
-
Cell signaling that recruits fibroblasts, keratinocytes, and endothelial cells to the wound site
-
Growth factor reservoirs that are released in a controlled manner as the matrix is remodeled
-
Regulation of protease activity, preventing the runaway tissue breakdown seen in chronic wounds
When skin is injured, the ECM is damaged alongside the epidermis and dermis. The speed and quality with which it is rebuilt — the remodeling phase — determines the final healing outcome.
The Four Phases of Wound Healing, and Where Collagen Remodeling Fits
-
Hemostasis — clot formation and initial matrix deposition
-
Inflammation — immune cells clear debris and pathogens
-
Proliferation — fibroblasts deposit new (largely Type III) collagen and angiogenesis begins
-
Remodeling — Type III collagen is progressively replaced by stronger Type I collagen, cross-linking increases, and tissue tensile strength is restored
This final phase can last from several weeks to over a year, and it is where most chronic wounds stall. In diabetic ulcers, venous ulcers, and pressure injuries, elevated protease activity (particularly matrix metalloproteinases) degrades the ECM faster than fibroblasts can rebuild it. The result is a wound trapped in a perpetual inflammatory loop — never progressing to organized remodeling.
Why an Intact ECM Scaffold Accelerates Remodeling
Clinical and pre-clinical research increasingly supports a straightforward principle: providing an intact, biologically active ECM scaffold at the wound site — rather than relying solely on the body’s own, often-compromised matrix — can shift a stalled wound back into a productive healing trajectory.
An effective ECM-based scaffold supports remodeling through several interconnected mechanisms:
-
Immunomodulation — moderating the inflammatory response so it resolves rather than persists
-
Protease regulation — controlling excess protease activity that would otherwise degrade newly formed collagen
-
Enhanced granulation and angiogenesis — supplying the vascular support new tissue needs
-
Organized re-epithelialization — guiding keratinocyte migration in a structured pattern that minimizes scarring
-
A moist, protected wound environment — the physical condition most conducive to cellular migration and matrix synthesis
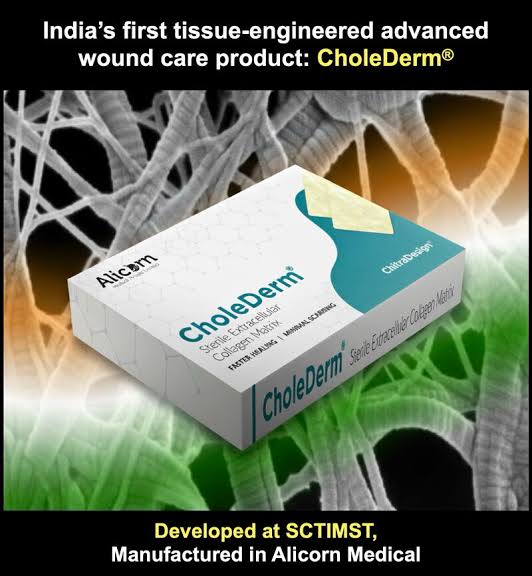
This is the scientific rationale behind tissue-engineered ECM scaffolds as a category, and it is the basis for how India’s own indigenous scaffold, CholeDerm®, was developed.
CholeDerm®: An Indigenous ECM Scaffold Built on This Science
CholeDerm® is manufactured by Alicorn Medical Private Limited, in collaboration with the Sree Chitra Tirunal Institute for Medical Sciences and Technology (SCTIMST), and holds the distinction of being India’s first tissue-engineered, CDSCO-approved (Class D) acellular scaffold of this kind.
What distinguishes CholeDerm® clinically is its manufacturing process — the patented PrisTINE Process — which is enzyme-free and detergent-free. Conventional decellularization methods often strip away the very biomolecules that drive remodeling. By avoiding aggressive enzymatic and detergent treatment, CholeDerm® preserves a matrix retaining 154 biomolecules relevant to wound healing, along with its native architecture.
In practical terms for a hospital wound care protocol, this means:
|
Clinical Need |
How CholeDerm® Addresses It |
|---|---|
|
Chronic inflammation in non-healing ulcers |
Immunomodulation balances the inflammatory response |
|
Excess protease activity degrading new tissue |
Regulates protease levels at the wound bed |
|
Poor vascularization delaying closure |
Enhances granulation and angiogenesis |
|
Disorganized healing and visible scarring |
Promotes structured, organized re-epithelialization |
|
Need for a stable, moist healing environment |
Maintains optimal moisture balance at the wound site |
CholeDerm® is indicated across a broad range of wound types relevant to multi-specialty hospital settings: diabetic ulcers, venous and chronic vascular ulcers, pressure ulcers, trauma wounds, surgical wounds (including donor sites, post-Mohs and post-laser surgery sites), and draining or tunneled wounds — making it applicable across dermatology, general surgery, plastic surgery, vascular surgery, and podiatry departments.
Why This Matters for Corporate Hospital Decision-Makers
For hospital administrators and clinical procurement teams evaluating advanced wound care formularies, the collagen remodeling science translates into measurable operational outcomes:
-
Reduced length of stay for chronic and non-healing wound admissions
-
Lower readmission rates tied to wound dehiscence and delayed healing
-
Improved patient-reported outcomes, particularly around scarring in plastic surgery and dermatology cases
-
A Made-in-India, cost-effective alternative to imported ECM scaffolds, supporting both procurement economics and self-reliance objectives
-
ISO 13485 compliance and CDSCO approval, meeting the regulatory bar required for tender and formulary inclusion
As more Indian hospitals build dedicated wound care centers and diabetic foot clinics, ECM-based scaffolds are shifting from a specialist tool to a standard-of-care consideration in advanced wound management protocols.
Conclusion
Collagen remodeling is the phase of healing that ultimately decides whether a wound closes cleanly or becomes a chronic clinical and financial burden. An intact, biologically preserved ECM scaffold gives that phase the structural and biochemical support it needs to proceed efficiently. CholeDerm®, developed indigenously and validated through India’s own regulatory and academic institutions, offers hospitals a clinically grounded, cost-effective way to bring this science into everyday wound care practice.
For clinical data, product specifications, or to arrange an evaluation for your hospital’s wound care or surgical department, hospitals can reach Alicorn Medical’s clinical team at technical@alicornmed.com or through the Sales and Customer Support desk at sales@alicornmed.com.